

Upper Lip Melasma: Causes, Chemical Peels, and Treatment Options
A “melasma mustache” can be triggered by sun exposure and influenced by hormones, family history, thyroid disease, or certain medications. It often appears as a brown or gray-brown patch above the lip, like a shadow. How to treat melasma on the upper lip starts with sun protection; topical treatments and carefully selected chemical peels may also help fade pigmentation.
If the patch is difficult to shift, you’re not alone. Upper-lip melasma can persist and may return after fading, particularly with sun exposure. Aggressive exfoliation or irritating treatments can worsen pigmentation, so a measured approach matters.
This article explains what upper-lip melasma looks like, why it can develop, and how sun protection, skincare ingredients, and chemical peels fit into treatment. It also covers why peels need careful consideration and how to support a more even-looking complexion over time.
Key Takeaways
- Learn what distinguishes upper-lip melasma from a temporary shadow and which changes may warrant closer attention.
- See how hormones, family history, medicines, and irritation from hair removal can contribute to pigmentation.
- Understand why chemical peels work by exfoliating the skin’s surface, and why a gentle approach matters.
- Find out how sunscreen ingredients, regular reapplication, and physical sun protection can help reduce common triggers.
- Compare topical options with oral or light-based treatments and understand why the right approach depends on the treatment’s risks and benefits.
Are there any cures or treatments for melasma?
Melasma has no cure, but sun protection and treatments can help lighten patches and limit recurrence. For upper-lip pigmentation, use daily sunscreen alongside shade and protective clothing.
Daily Sun Protection
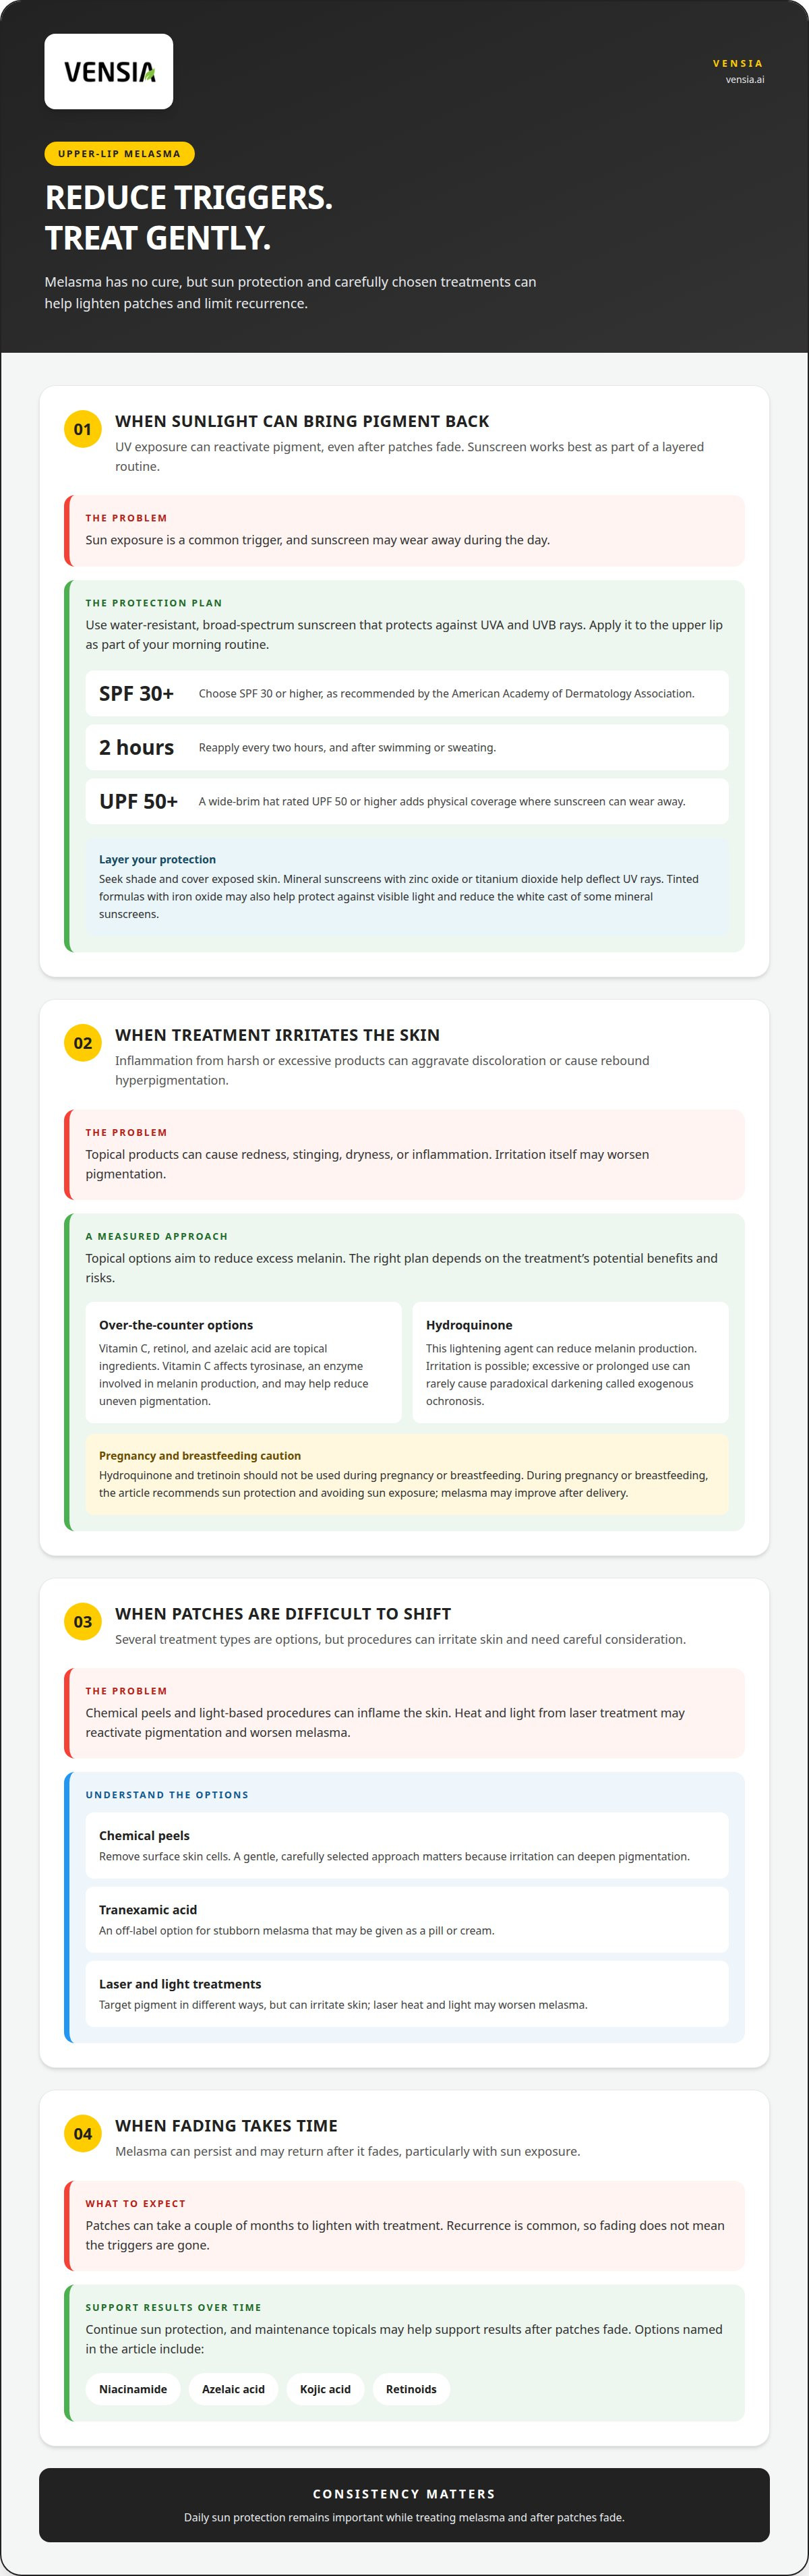
Daily sun protection means using broad-spectrum sunscreen that shields skin from UVA and UVB rays. Choose water-resistant sunscreen with SPF 30 or higher, as recommended by the American Academy of Dermatology Association. Apply it to the upper lip as part of your morning routine, then reapply every two hours and after swimming or sweating. Consistency matters because UV exposure can reactivate pigment even after patches fade.
Mineral sunscreens containing zinc oxide or titanium dioxide sit on the skin and help deflect UV rays. Tinted formulas with iron oxide may also help protect against visible light and reduce the white cast some mineral sunscreens leave. Sunscreen alone isn’t complete protection: seek shade and cover exposed skin, especially when spending extended time outdoors.
Treatment may also include topical agents such as hydroquinone, which can reduce melanin production. However, irritating products or aggressive treatments can trigger inflammation and rebound hyperpigmentation. There’s no single treatment plan for everyone, and ongoing sun protection remains important even when a topical treatment lightens the pigment.
In the United States, dermatologist visits and melasma treatment costs depend on the type of appointment and treatments included in a care plan. Costs can differ between topical treatments and procedures, or when a plan combines approaches.
Sun Avoidance and Protective Clothing
Sun avoidance and protective clothing reduce the UV reaching the upper lip by combining shade with physical coverage. A Cleveland Clinic dermatologist recommends a wide-brim hat rated UPF 50 or higher for sun protection. A hat adds a barrier where sunscreen can wear away.
Build these measures into your daily routine: choose shade for outdoor breaks, wear a hat in direct sun, and keep sunscreen handy for reapplication. Cloudy skies and winter conditions don’t eliminate the need for year-round protection, since UV light can still affect skin. This layered approach helps reduce triggers that may cause upper-lip pigmentation to return.
What causes a melasma mustache?
Upper-lip melasma can develop through a combination of sun exposure, hormonal changes, family history, thyroid disease, and certain medications. Irritation from hair removal or skincare products can also worsen hyperpigmentation, especially when the area is then exposed to sunlight.
Treatment aims to reduce excess melanin and limit triggers. Topical products, oral medicines, chemical peels, and light-based procedures are options, but irritation from some treatments can deepen pigmentation or cause it to return. Understanding how to treat melasma on the upper lip starts with identifying factors that may be driving the discoloration.
Over-the-counter topical ingredients include vitamin C, retinol, and azelaic acid. Vitamin C affects tyrosinase, an enzyme involved in melanin production, and may help reduce uneven pigmentation. Hydroquinone is another lightening agent used in prescription creams. It can reduce melanin production, but excessive or prolonged use can cause irritation or, rarely, paradoxical darkening called exogenous ochronosis.
Some treatment plans combine ingredients. Dermatologists may prescribe a triple-combination cream containing hydroquinone, tretinoin, and fluocinolone. Hydroquinone and tretinoin shouldn’t be used during pregnancy or breastfeeding. Topical treatments can also cause redness, stinging, dryness, or inflammation; irritation itself may aggravate discoloration.
For stubborn melasma, tranexamic acid is an off-label option that may be given as a pill or cream. Chemical peels remove surface skin cells, while laser and light treatments target pigment in different ways. These procedures can irritate skin, and laser treatment can worsen melasma because heat and light may reactivate pigmentation.
Melasma patches can take a couple of months to lighten with treatment. Recurrence is common, so continued sun protection and maintenance topicals, including niacinamide, azelaic acid, kojic acid, or retinoids, can help support results after patches fade. When considering how to treat melasma on the upper lip, remember that ongoing protection is part of managing recurrence.
Topical treatment risks include irritation and rebound hyperpigmentation, particularly with harsh or excessive use. Chemical peels and light-based procedures can also inflame the skin, so treatment strength and your skin’s response matter.
For a separate body-care step, VENSIA Niacinamide Marshmallow Body Lotion is designed to moisturize and soothe dry, rough body skin; it isn’t an upper-lip melasma treatment.
Sun exposure, family history, hormones, thyroid disease and medications
Upper-lip melasma often reflects several influences rather than one isolated cause. Sun exposure, hormonal changes, inherited susceptibility, thyroid disease, and certain medications can each contribute.
During pregnancy or breastfeeding, the recommended approach is sun protection and avoiding sun exposure; melasma may improve after delivery. Hydroquinone and tretinoin should not be used during pregnancy or breastfeeding.
Hormonal and Genetic Factors
Hormonal and genetic factors can make pigment-producing cells more responsive to triggers. Melasma is more common in women, and fluctuating estrogen levels may contribute to its development. Pregnancy-related changes in estrogen and progesterone can also play a role, while birth control pills or hormone replacement therapy may trigger patches in people predisposed to melasma. A family history can indicate inherited susceptibility.
Hormonal influences don’t explain every case. Upper-lip discoloration can develop without pregnancy or hormone therapy, particularly when other triggers are present. Menopause can also involve hormonal changes associated with melasma. These connections matter because pigmentation may persist while a trigger remains active, even when a topical product lightens the visible patch.
Other Melasma Triggers
Other triggers include ultraviolet exposure, thyroid disease, medications that increase skin photosensitivity, and irritation. Sunlight can stimulate melanin production, and exposure may bring back pigment after it fades. Irritation from harsh cleansers, exfoliants, or upper-lip hair removal can also aggravate discoloration, especially when the area is then exposed to sunlight.
Thyroid disease and some medications have been linked to melasma, but that doesn’t mean you should stop a prescribed medicine. If pigmentation appears after starting a medication, discuss the timing and possible alternatives with the prescribing clinician. A dermatologist can assess your skin and consider the pattern, medical history, and possible triggers together.
Notice what changes around the time pigmentation develops. A new hair-removal routine, medication change, or increase in outdoor exposure, for example, may help explain why a patch appeared or became more noticeable. These details don’t prove a cause, but they give a dermatologist useful context.
Reducing avoidable irritation and maintaining sun protection can address triggers even when hormones or family history also contribute. If the upper lip becomes irritated after using a product or removing hair, pause the irritating routine and avoid adding harsh exfoliants. Persistent or changing pigmentation deserves assessment, since a dermatologist can distinguish melasma from other causes of facial discoloration.
Chemical peels
A chemical peel exfoliates the skin’s top layer, encouraging newer skin with a more even tone. For upper-lip melasma, this may improve the appearance of excess pigment, but it doesn’t remove the underlying causes. Melasma can recur, so a peel is one possible treatment, not a permanent cure.
Salicylic acid exfoliates by removing dead surface cells and encouraging their replacement. This helps explain why it may be used in a peel for discoloration. The goal is measured renewal, not aggressive removal: treating a melasma mustache too forcefully can inflame the skin and make hyperpigmentation more noticeable.
Peel ingredients and intensity should suit the treated area and the person’s skin. The upper lip is a small, visible area, so irritation there can be especially noticeable. Sensitive skin is a reason to avoid chemical peels, as irritation may follow. A dermatologist can assess the pigmentation and skin response when weighing a peel against topical treatments such as retinoids.
Dr. Scott Gerrish advises treating hyperpigmented areas lightly over multiple treatments. This avoids concentrating too much activity in one session, which can trigger inflammation and worsen melasma. No treatment schedule or peel strength suits everyone; skin sensitivity and prior reactions matter. Don’t treat a stronger peel as a shortcut to faster lightening.
Peels can cause irritation, and irritation itself may lead to rebound hyperpigmentation. The same concern applies to other treatments, including whitening agents, lasers, and light therapy. If the skin becomes inflamed, the original pigment may darken or become harder to manage. People with sensitive skin should avoid peels rather than risk adding irritation to an already discolored area.
Sun exposure also matters because it can activate pigmentation and contribute to melasma returning. A peel doesn’t replace sun protection, and fading after treatment doesn’t mean the trigger has disappeared. Keeping the area protected helps limit renewed pigment as the skin’s appearance changes. This is especially important for upper-lip melasma, which can be persistent and difficult to treat.
Consider a peel as one part of a broader plan, not a stand-alone solution. Relevant factors include the peel’s ingredients, skin sensitivity, existing irritation, and the risk of worsening discoloration. Gentle treatment over multiple sessions may be preferable to aggressive action, while topical options offer another route to lightening. The aim is to improve tone without provoking more pigmentation.
What melasma looks like on the upper lip
Upper-lip melasma appears as darkened patches caused by increased pigmentation in the skin. The discoloration may form a band above the lip, creating the “melasma mustache” appearance, or appear as separate areas. Patches can be symmetrical or asymmetrical, and may also occur on the cheeks, forehead, or sides of the face.
A key visual clue is persistent discoloration on a sun-exposed area, rather than a temporary shadow that changes with the lighting. Melasma can appear alone or alongside patches elsewhere on the face. Its appearance reflects excess pigment, but color and shape alone can’t confirm the cause.
Melasma is acquired hypermelanosis, meaning the skin develops excess pigmentation after birth. It isn’t skin cancer. Typical patches don’t cause pain, itching, inflammation, or other discomfort, so irritation or soreness isn’t a defining feature of melasma.
Sun exposure can darken existing patches by stimulating melanin production. A patch may look more noticeable after time outdoors, then fade somewhat when exposure decreases. That change doesn’t necessarily mean the underlying tendency has disappeared; melasma can recur, often in the same area.
Other facial pigmentation can resemble a mustache-like shadow, so appearance isn’t a reliable basis for self-diagnosis. A dermatologist diagnoses melasma based on its clinical appearance and can assess whether the pattern fits. This is especially useful when a patch is new, persistent, or difficult to distinguish from other causes of discoloration.
See a dermatologist if an upper-lip patch is painful, itchy, inflamed, or otherwise uncomfortable, since those symptoms aren’t typical of melasma. Also seek an assessment if the cause of persistent discoloration is unclear. A clinical evaluation helps distinguish melasma from other skin changes before you choose a lightening approach.
Pay attention to how the patch changes over time. Note, for example, whether the upper-lip area darkens after sun exposure or becomes irritated following hair removal or a skincare product. These observations can help identify possible triggers, but they don’t establish a diagnosis or replace a dermatologist’s assessment.
Because melasma can return after fading, a clearer appearance doesn’t mean the pigment-producing response has stopped. Ongoing sun protection remains relevant, even when the patch looks lighter. For a related skin-care option, explore products for uneven skin tone.
VENSIA
VENSIA offers skincare options for concerns such as dark spots and uneven skin tone. VENSIA Anti-Pigmentation Cream is formulated for dark spots and an even-looking complexion, making it a relevant skincare option when pigmentation is a concern. It shouldn’t be presented as a cure for melasma or a replacement for sun protection. Melasma can recur, and a dermatologist can assess persistent or changing patches and discuss suitable treatment options.
Choose skincare carefully around the upper lip, where irritation may make discoloration more noticeable. Follow the product directions and discontinue use if irritation develops. For a persistent patch, prioritize professional assessment rather than relying on cosmetic products alone. Contact VENSIA to learn more about its skincare options for pigmentation concerns.
Build a Steady Path Toward More Even-Looking Skin
Choosing how to treat melasma on the upper lip isn’t about pursuing the strongest product or quickest change. Keep your routine gentle, notice how your skin responds, and avoid adding several new products at once. This makes it easier to recognize irritation and adjust your care without adding stress for sensitive skin.
Let your priorities guide your skincare choices. If your focus is uneven tone, explore options designed for pigmentation concerns and consider how they fit into your existing routine. Persistent or changing patches call for professional assessment, rather than relying on cosmetic skincare alone.
For a calm next step, talk with VENSIA about your skincare options. Choose a routine that feels manageable, give your skin consistent care, and move forward with patience. Small, considered choices can help you feel more confident in the way you care for your skin.
Frequently Asked Questions
Does the condition worsen during certain seasons?
Melasma may become more noticeable in summer, when people often spend more time outdoors and get greater sun exposure. A patch can also darken after sunny days, even if it looked lighter before. Keep sun protection consistent through seasonal changes, including cloudy periods and winter, rather than starting only when the weather feels hot. Outdoor routines and time in direct sunlight can matter more than the calendar.
How can I reduce the likelihood of melasma?
Reduce common triggers by making sun protection part of your routine, even when you don’t plan a long outdoor outing. Apply sunscreen over the upper lip, reapply after sweating, and use a hat or shade in direct sunlight. Avoid harsh exfoliants or products that leave the skin irritated. If hair removal repeatedly causes redness, consider whether it may be adding irritation before sun exposure.
How would I know if I have melasma, and how is it diagnosed?
Melasma often appears as persistent brown or gray-brown patches on the face, including above the lip, and usually doesn’t cause discomfort. Appearance alone can’t establish a diagnosis because other skin changes may also cause dark patches. A dermatologist assesses the pattern and clinical appearance, as well as where the discoloration occurs and any relevant skin history. Seek assessment if the patch is changing or its cause is unclear.
Upper Lip Melasma: How Do You Get Rid of It?
There’s no permanent cure, but treatment can help lighten upper-lip patches and manage recurrence. Sun protection is the foundation; topical ingredients such as azelaic acid or vitamin C may also be considered. Prescription options and procedures require careful assessment because irritation can worsen pigmentation. Avoid trying several strong products at once, especially on sensitive skin. A dermatologist can distinguish melasma from other discoloration before treatment begins.
What are the triggers for melasma?
Common triggers include sunlight, hormonal changes, family predisposition, thyroid disease, and some medications that increase skin photosensitivity. Irritation from skincare products or upper-lip hair removal can also contribute to darker patches, particularly when followed by sun exposure. Triggers can overlap: someone with a family history may notice pigmentation after a hormonal change and increased time outdoors. Note changes in routines or medicines to discuss with a clinician.
Who does it affect and why?
Melasma can affect people of any background, but it is more common in women and people with darker skin tones or a family history. Hormonal fluctuations may contribute, including changes associated with pregnancy, birth control pills, or hormone replacement therapy. Melasma can also occur in people who aren’t pregnant. These factors raise susceptibility, but they don’t predict exactly who will develop patches or when.
Why does a melasma moustache appear?
The “melasma moustache” describes pigmentation concentrated above the upper lip, where it can create a shadow-like band. Melasma affects pigment in the skin, and sunlight can make the area more noticeable by stimulating pigment production. The patch may appear alone or alongside discoloration on the cheeks or forehead. Its position can resemble a facial-hair shadow, but that appearance alone doesn’t confirm melasma.
How can you tell upper-lip melasma from post-inflammatory hyperpigmentation or other skin conditions?
It can be difficult to distinguish these conditions by appearance alone. Post-inflammatory hyperpigmentation can follow irritation or skin injury, while melasma often appears as persistent facial patches; both can look darker than the surrounding skin. Melasma usually doesn’t cause pain, itching, or inflammation. A dermatologist can assess the patch’s pattern and history to identify the likely cause, particularly if it appeared after a reaction or keeps changing.


